
1. Chapter at a Glance
Oxygen is used by organisms to break down simple molecules like glucose, amino acids and fatty acids to release energy for various activities. Carbon dioxide, which is harmful, is released during these catabolic reactions. So O₂ must be continuously supplied to cells and CO₂ removed. This exchange of O₂ from the atmosphere with CO₂ produced by cells is called breathing, commonly known as respiration. This chapter covers respiratory organs in animals, the human respiratory system, the mechanism of breathing, respiratory volumes and capacities, the exchange and transport of gases, the regulation of breathing, and common disorders. NEET asks about two questions every year, usually on lung volumes, partial pressures, the oxygen dissociation curve and transport of CO₂.
- Respiratory organs of different animals (skin, tracheae, gills, lungs).
- Parts of the human respiratory system; the conducting and exchange parts.
- Inspiration and expiration — role of diaphragm and intercostal muscles.
- Values of TV, IRV, ERV, RV and the capacities (VC, TLC, FRC, IC, EC).
- Partial pressures of O₂ and CO₂; the sigmoid oxygen dissociation curve and factors shifting it.
- Transport of CO₂ as bicarbonate (carbonic anhydrase), regulation by the medulla and pons, and disorders (asthma, emphysema).
2. Respiratory Organs
Mechanisms of breathing vary among different groups of animals, depending mainly on their habitats and levels of organisation.
| Animal group | Respiratory surface | NEET Note |
|---|---|---|
| Sponges, coelenterates, flatworms | Simple diffusion over the entire body surface | Lower invertebrates |
| Earthworms | Moist cuticle | Cutaneous respiration |
| Insects | Network of tubes (tracheal tubes) | Air carried directly to tissues |
| Most aquatic arthropods and molluscs | Gills (branchial respiration) | — |
| Fishes | Gills | — |
| Terrestrial forms (reptiles, birds, mammals) | Lungs (pulmonary respiration) | — |
| Amphibians such as frogs | Lungs and moist skin (cutaneous) | Both |
3. Human Respiratory System
- A pair of external nostrils opens out above the upper lips. It leads to a nasal chamber through the nasal passage. The nasal chamber opens into the pharynx, a common passage for food and air.
- The pharynx opens through the larynx region into the trachea. The larynx is a cartilaginous box that helps in sound production and is therefore called the sound box.
- During swallowing, the glottis can be covered by a thin elastic cartilaginous flap called the epiglottis, preventing food from entering the larynx.
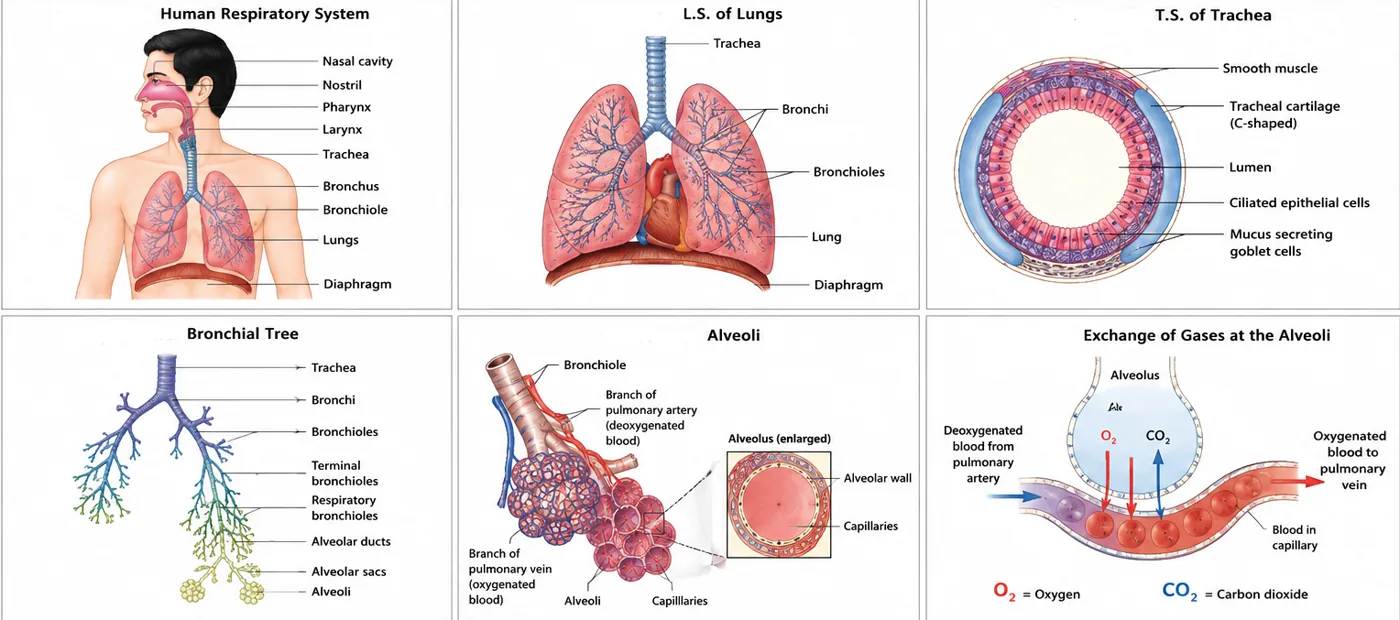
- The trachea is a straight tube extending up to the mid-thoracic cavity. It divides at the level of the 5th thoracic vertebra into a right and left primary bronchus. Each bronchus undergoes repeated divisions to form secondary and tertiary bronchi and bronchioles, ending in very thin terminal bronchioles.
- The trachea, primary, secondary and tertiary bronchi and initial bronchioles are supported by incomplete cartilaginous rings.
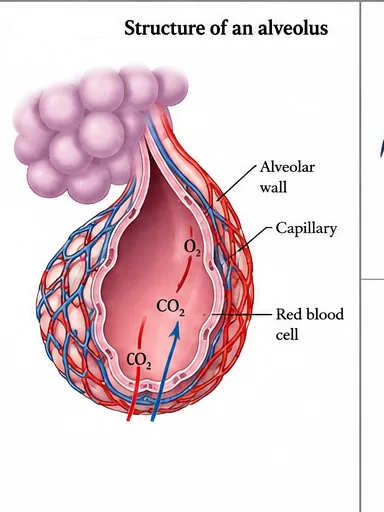
- Each terminal bronchiole gives rise to a number of very thin, irregular-walled, vascularised bag-like structures called alveoli. The branching network of bronchi, bronchioles and alveoli makes up the lungs.
- The lungs are covered by a double-layered pleura with pleural fluid between the layers, which reduces friction on the lung surface. The outer pleural membrane is in close contact with the thoracic lining; the inner membrane is in contact with the lung surface.
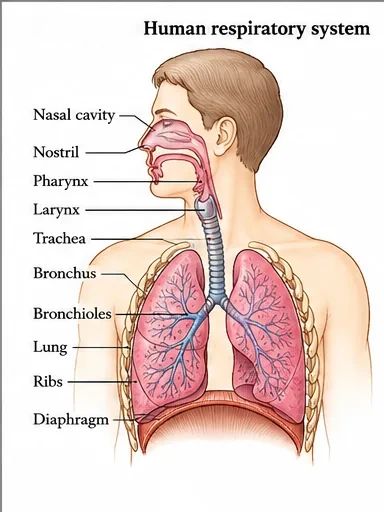
- The part from the external nostrils up to the terminal bronchioles is the conducting part. It transports atmospheric air to the alveoli, clears it of foreign particles, humidifies it and brings it to body temperature.
- The alveoli and their ducts form the respiratory or exchange part. This is the site of actual diffusion of O₂ and CO₂ between blood and atmospheric air.
The lungs are situated in the thoracic chamber, which is anatomically an air-tight chamber. It is formed dorsally by the vertebral column, ventrally by the sternum, laterally by the ribs, and on the lower side by the dome-shaped diaphragm. Because of this arrangement, any change in the volume of the thoracic cavity is reflected in the lung (pulmonary) cavity. Such an arrangement is essential for breathing, since we cannot directly alter the pulmonary volume.
Steps of respiration: (i) breathing or pulmonary ventilation, by which atmospheric air is drawn in and CO₂-rich alveolar air is released; (ii) diffusion of gases (O₂ and CO₂) across the alveolar membrane; (iii) transport of gases by the blood; (iv) diffusion of O₂ and CO₂ between blood and tissues; (v) utilisation of O₂ by the cells for catabolic reactions, releasing CO₂ (cellular respiration).
4. Mechanism of Breathing
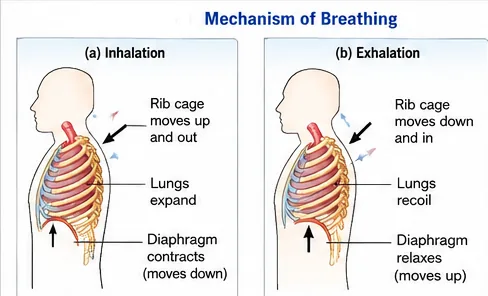
Breathing involves two stages: inspiration, during which atmospheric air is drawn in, and expiration, by which alveolar air is released. Air moves because a pressure gradient is created between the lungs and the atmosphere.
| Feature | Inspiration | Expiration |
|---|---|---|
| Diaphragm | Contracts, flattens (moves down); volume increases in the antero-posterior axis | Relaxes, returns to dome shape (moves up) |
| External intercostal muscles | Contract, lifting ribs and sternum; volume increases in the dorso-ventral axis | Relax; ribs and sternum return |
| Thoracic and pulmonary volume | Increases | Decreases |
| Intra-pulmonary pressure | Falls below atmospheric pressure | Rises slightly above atmospheric pressure |
| Air movement | Into the lungs | Out of the lungs |
| NEET Note | Active process | Normally passive (forceful expiration uses internal intercostals and abdominal muscles) |
- We can increase the strength of inspiration and expiration with the help of additional muscles in the abdomen.
- On average, a healthy human breathes 12–16 times per minute.
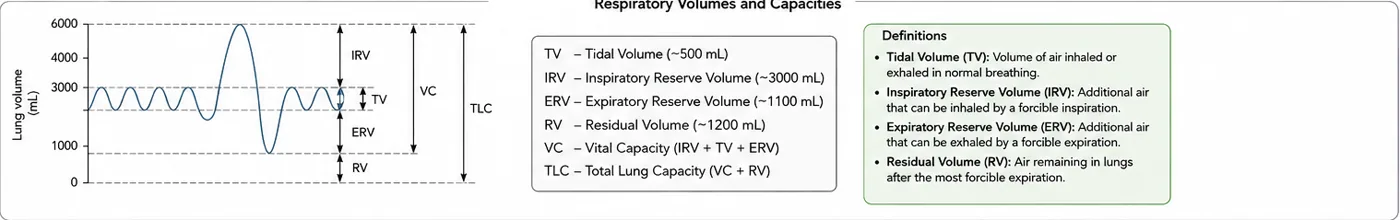
- The volume of air involved in breathing movements can be estimated with a spirometer, which helps in the clinical assessment of pulmonary functions.
5. Respiratory Volumes and Capacities
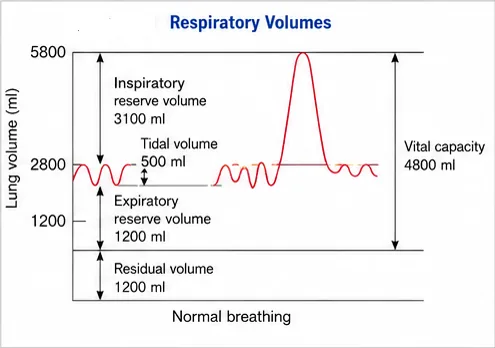
| Volume / capacity | Definition | Approximate value |
|---|---|---|
| Tidal volume (TV) | Air inspired or expired during a normal respiration | 500 mL (6000–8000 mL per minute) |
| Inspiratory reserve volume (IRV) | Additional air that can be inspired by a forcible inspiration | 2500–3000 mL |
| Expiratory reserve volume (ERV) | Additional air that can be expired by a forcible expiration | 1000–1100 mL |
| Residual volume (RV) | Air remaining in the lungs even after a forcible expiration | 1100–1200 mL |
| Inspiratory capacity (IC) | TV + IRV | About 3000–3500 mL |
| Expiratory capacity (EC) | TV + ERV | About 1500–1600 mL |
| Functional residual capacity (FRC) | ERV + RV — air left after a normal expiration | About 2100–2300 mL |
| Vital capacity (VC) | ERV + TV + IRV — maximum air a person can breathe in after a forced expiration (or breathe out after a forced inspiration) | About 4000–4600 mL |
| Total lung capacity (TLC) | VC + RV — total air accommodated in the lungs after a forced inspiration | About 5100–5800 mL |
6. Exchange of Gases
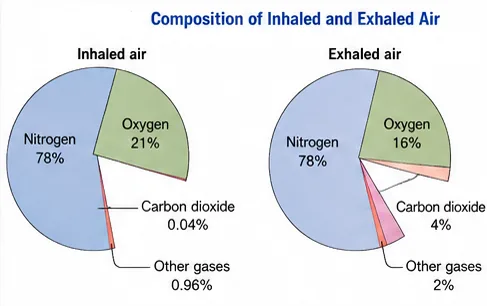
Alveoli are the primary sites of exchange of gases. Exchange also occurs between blood and tissues. O₂ and CO₂ are exchanged at these sites by simple diffusion, based mainly on pressure (concentration) gradients. Solubility of the gases and the thickness of the membranes are also important factors.
- The pressure contributed by an individual gas in a mixture is called its partial pressure (pO₂ for oxygen, pCO₂ for carbon dioxide).
- The solubility of CO₂ is 20–25 times higher than that of O₂, so the amount of CO₂ that can diffuse through the diffusion membrane per unit difference in partial pressure is much higher.
- The diffusion membrane is made of three major layers: the thin squamous epithelium of alveoli, the endothelium of alveolar capillaries, and the basement substance between them. Its total thickness is much less than a millimetre.
| Gas | Atmospheric air | Alveoli | Deoxygenated blood | Oxygenated blood | Tissues |
|---|---|---|---|---|---|
| O₂ (mm Hg) | 159 | 104 | 40 | 95 | 40 |
| CO₂ (mm Hg) | 0.3 | 40 | 45 | 40 | 45 |
7. Transport of Gases
Blood is the medium of transport for O₂ and CO₂.
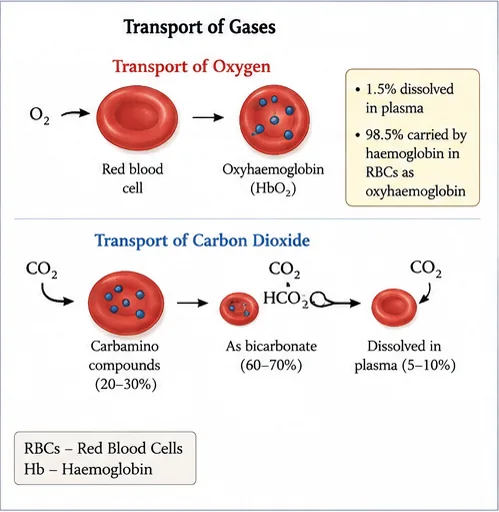
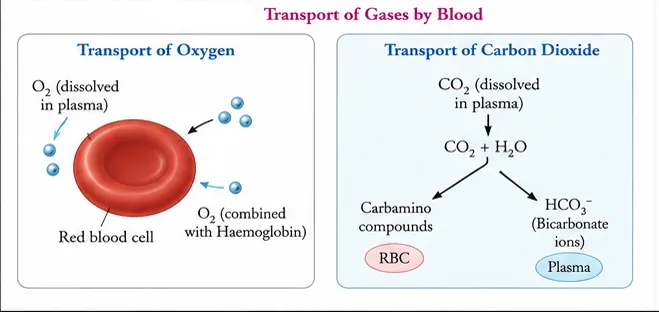
- About 97% of O₂ is transported by RBCs in the blood. The remaining 3% is carried in a dissolved state through the plasma.
- Nearly 20–25% of CO₂ is transported by RBCs (as carbamino-haemoglobin), about 70% is carried as bicarbonate, and about 7% is carried in a dissolved state through plasma.
Transport of oxygen
- Haemoglobin is a red, iron-containing pigment present in the RBCs. O₂ can bind with haemoglobin in a reversible manner to form oxyhaemoglobin. Each haemoglobin molecule can carry a maximum of four molecules of O₂.
- Binding of oxygen with haemoglobin is primarily related to the partial pressure of O₂. Partial pressure of CO₂, hydrogen ion concentration and temperature also interfere with this binding.
- A sigmoid curve is obtained when percentage saturation of haemoglobin with O₂ is plotted against pO₂. This curve is called the oxygen dissociation curve, and it is highly useful in studying the effect of factors like pCO₂ and H⁺ concentration on binding of O₂ with haemoglobin.
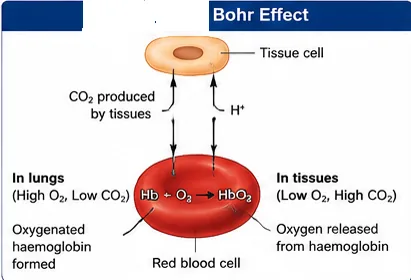
- In the alveoli — high pO₂, low pCO₂, lower H⁺ concentration and lower temperature — conditions favour the formation of oxyhaemoglobin. In the tissues — low pO₂, high pCO₂, high H⁺ concentration and higher temperature — conditions favour the dissociation of oxygen from oxyhaemoglobin.
- Under normal physiological conditions, every 100 mL of oxygenated blood can deliver around 5 mL of O₂ to the tissues.
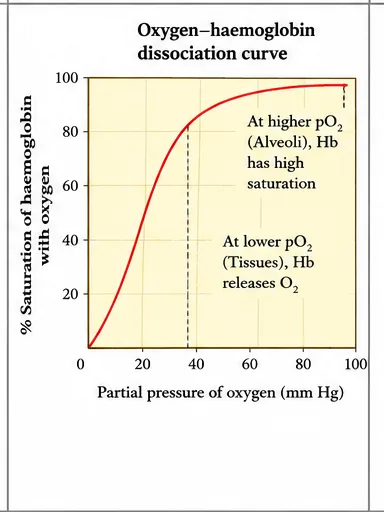
The effect of CO₂ and H⁺ on the curve is called the Bohr effect. High pCO₂ and H⁺ (low pH) and high temperature shift the curve to the right (Hb gives up O₂ more easily — good for tissues). Low pCO₂, high pH and low temperature shift it to the left (Hb holds O₂ more tightly — good for loading in lungs).
Transport of carbon dioxide
- CO₂ is carried by haemoglobin as carbamino-haemoglobin (about 20–25%). This binding depends on pCO₂; pO₂ is a major factor that affects it. When pCO₂ is high and pO₂ is low, as in tissues, more CO₂ binds; in the alveoli, where pCO₂ is low and pO₂ is high, CO₂ dissociates from carbamino-haemoglobin.
- RBCs contain a very high concentration of the enzyme carbonic anhydrase; a minute quantity is present in plasma too. It facilitates the reaction in both directions:
- At the tissue site, where pCO₂ is high due to catabolism, CO₂ diffuses into blood (RBCs and plasma) and forms HCO₃⁻ and H⁺. At the alveolar site, where pCO₂ is low, the reaction proceeds in the opposite direction, forming CO₂ and H₂O.
- CO₂ trapped as bicarbonate at the tissue level and transported to the alveoli is released as CO₂. Every 100 mL of deoxygenated blood delivers approximately 4 mL of CO₂ to the alveoli.
8. Regulation of Respiration
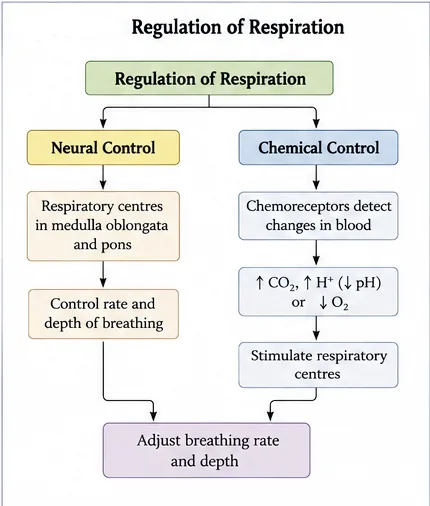
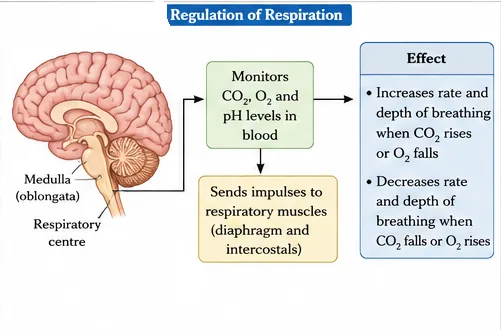
- Human beings can moderate the respiratory rhythm to suit the demands of the body tissues. This is done by the neural system.
- A specialised centre in the medulla region of the brain called the respiratory rhythm centre is primarily responsible for this regulation.
- Another centre in the pons region, called the pneumotaxic centre, can moderate the functions of the respiratory rhythm centre. Neural signals from it can reduce the duration of inspiration and thereby alter the respiratory rate.
- A chemosensitive area situated adjacent to the rhythm centre is highly sensitive to CO₂ and hydrogen ions. An increase in these substances activates this centre, which signals the rhythm centre to make adjustments so that these substances can be eliminated.
- Receptors associated with the aortic arch and carotid artery also recognise changes in CO₂ and H⁺ concentration and send signals to the rhythm centre for remedial action.
- The role of oxygen in the regulation of respiratory rhythm is quite insignificant.
9. Disorders of the Respiratory System
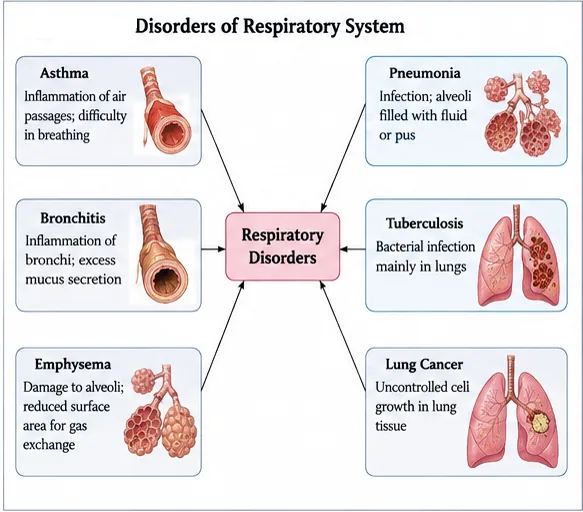
| Disorder | Cause / feature | NEET Note |
|---|---|---|
| Asthma | Difficulty in breathing causing wheezing, due to inflammation of bronchi and bronchioles | Often allergic |
| Emphysema | Chronic disorder in which alveolar walls are damaged, decreasing the respiratory surface | Cigarette smoking is a major cause |
| Occupational respiratory disorders | In industries involving grinding or stone-breaking, so much dust is produced that defence mechanisms cannot cope. Long exposure causes inflammation leading to fibrosis (proliferation of fibrous tissue) and serious lung damage. | Workers should wear protective masks |
| Bronchitis, pneumonia, tuberculosis, lung cancer | Inflammation of bronchi; infection filling alveoli with fluid; bacterial infection (Mycobacterium tuberculosis); uncontrolled growth of lung cells | General awareness |
10. Master Summary Table
| Topic | Key fact | NEET Note |
|---|---|---|
| Trachea divides | At 5th thoracic vertebra | Incomplete cartilage rings |
| Conducting part | Nostrils to terminal bronchioles | Filters, humidifies, warms air |
| Exchange part | Alveoli and ducts | Diffusion membrane < 1 mm |
| Inspiration | Diaphragm + external intercostals contract | Active |
| Tidal volume | 500 mL | 6000–8000 mL per minute |
| Vital capacity | ERV + TV + IRV | About 4000–4600 mL |
| pO₂ alveoli / tissues | 104 / 40 mm Hg | pCO₂ 40 / 45 |
| O₂ transport | 97% as oxyhaemoglobin | Each Hb carries 4 O₂ |
| CO₂ transport | ~70% as bicarbonate | Carbonic anhydrase in RBCs |
| Regulation | Medulla (rhythm), pons (pneumotaxic) | CO₂ and H⁺ main signals |
| Emphysema | Alveolar walls damaged | Smoking |
11. Mind Map
- Respiratory organs
- Human system
- Pleura, thorax
- Inspiration
- Expiration
- Volumes, capacities
- Partial pressures
- O₂ dissociation curve
- CO₂ as HCO₃⁻
- Medulla, pons
- Chemoreceptors
- Asthma, emphysema
12. Tips and Tricks
- Every capacity is a sum of two or more volumes.
- "Vital = eVerything except residual" (VC = TLC − RV).
- FRC = ERV + RV (air left after a normal breath out). IC = TV + IRV.
- Bohr effect: "CADET, face Right" — CO₂, Acid, 2,3-DPG, Exercise and Temperature shift the curve to the right.
- Partial pressures: O₂ "104 – 40 – 95 – 40"; CO₂ "40 – 45 – 40 – 45".
- Thinking the residual volume can be breathed out.
- Saying O₂ is the main chemical regulator of breathing (it is CO₂ and H⁺).
- Saying CO₂ is mostly carried as carbamino-haemoglobin (most is bicarbonate).
- Placing the pneumotaxic centre in the medulla (it is in the pons).
- Calling normal expiration an active process.
13. Important One-liners
- Insects respire through a network of tracheal tubes.
- The larynx is called the sound box.
- The epiglottis prevents entry of food into the larynx.
- A healthy human breathes 12–16 times a minute.
- The volume of air in breathing is measured with a spirometer.
- CO₂ is 20–25 times more soluble than O₂.
- Each haemoglobin molecule can carry four oxygen molecules.
- Every 100 mL of oxygenated blood delivers about 5 mL of O₂ to tissues.
- Every 100 mL of deoxygenated blood delivers about 4 mL of CO₂ to alveoli.
- The respiratory rhythm centre is in the medulla oblongata.
- Emphysema reduces the respiratory surface of the lungs.
14. NEET-pattern Questions with Detailed Answers
These questions are original and based on concepts that NEET UG asks again and again.
The volume of air remaining in the lungs after a forcible expiration is:
- Tidal volume
- Residual volume
- Expiratory reserve volume
- Vital capacity
Show solution
Residual volume (1100–1200 mL) stays in the lungs even after the hardest possible breath out. Tidal volume is a normal breath, ERV is the extra air that can be forced out, and vital capacity is the maximum air exchanged.
Answer: (B)
Most of the CO₂ in blood is transported as:
- Carbamino-haemoglobin
- Dissolved CO₂
- Bicarbonate ions
- Carbonic acid
Show solution
About 70% of CO₂ travels as bicarbonate, formed with the help of carbonic anhydrase. About 20–25% is carried as carbamino-haemoglobin and about 7% is dissolved in plasma.
Answer: (C)
Vital capacity of the lungs equals:
- TV + IRV
- TV + IRV + ERV
- ERV + RV
- TV + IRV + ERV + RV
Show solution
VC is the maximum air that can be breathed in after a forced expiration, which is ERV + TV + IRV. TV + IRV is the inspiratory capacity, ERV + RV is the FRC, and adding RV to VC gives the TLC.
Answer: (B)
The partial pressure of oxygen in the alveoli and in the tissues is, respectively:
- 104 and 40 mm Hg
- 40 and 104 mm Hg
- 95 and 45 mm Hg
- 159 and 40 mm Hg
Show solution
Alveolar pO₂ is 104 mm Hg and tissue pO₂ is 40 mm Hg, so O₂ flows from the lungs to the tissues. The value 159 is for atmospheric air, and 95 is for oxygenated blood.
Answer: (A)
Which factor shifts the oxygen dissociation curve to the right?
- Low pCO₂
- High pH
- High temperature
- Low H⁺ concentration
Show solution
High temperature, high pCO₂ and high H⁺ (low pH) lower haemoglobin's affinity for O₂, shifting the curve to the right so O₂ is unloaded in tissues. The other three options shift the curve to the left.
Answer: (C)
The pneumotaxic centre, which can reduce the duration of inspiration, is located in the:
- Medulla oblongata
- Pons
- Cerebellum
- Hypothalamus
Show solution
The pneumotaxic centre is in the pons and moderates the respiratory rhythm centre in the medulla. The cerebellum and hypothalamus have no direct role in the respiratory rhythm.
Answer: (B)
Assertion (A): During inspiration, the intra-pulmonary pressure becomes lower than the atmospheric pressure.
Reason (R): Contraction of the diaphragm and external intercostal muscles increases the volume of the thoracic cavity.
- Both A and R are true, and R explains A
- Both A and R are true, but R does not explain A
- A is true, R is false
- A is false, R is true
Show solution
The increase in thoracic and pulmonary volume lowers the pressure inside the lungs below atmospheric pressure, so air rushes in. R is the cause of A.
Answer: (A)
A person has TV = 500 mL, IRV = 2500 mL, ERV = 1000 mL and RV = 1200 mL. What is the functional residual capacity?
- 1500 mL
- 2200 mL
- 3000 mL
- 4000 mL
Show solution
FRC = ERV + RV = 1000 + 1200 = 2200 mL. The other options are different capacities: EC = TV + ERV = 1500 mL, IC = TV + IRV = 3000 mL, and VC = 4000 mL.
Answer: (B)
Which statement about gas exchange is correct?
- CO₂ is less soluble than O₂, so it diffuses more slowly
- The diffusion membrane is about one centimetre thick
- CO₂ is 20–25 times more soluble than O₂, so it diffuses faster per unit pressure difference
- Exchange of gases is an active process
Show solution
CO₂'s much higher solubility lets far more of it diffuse for a small pressure difference (45 versus 40 mm Hg). The membrane is less than a millimetre thick, and gas exchange happens by simple, passive diffusion.
Answer: (C)
Match: (a) Emphysema (b) Asthma (c) Fibrosis (d) Carbonic anhydrase — (i) Inflammation of bronchi and bronchioles (ii) Damage to alveolar walls (iii) Occupational dust exposure (iv) Enzyme in RBCs.
- a-ii, b-i, c-iii, d-iv
- a-i, b-ii, c-iv, d-iii
- a-iii, b-i, c-ii, d-iv
- a-ii, b-iii, c-i, d-iv
Show solution
In emphysema the alveolar walls are damaged. Asthma is inflammation of the bronchi and bronchioles. Fibrosis results from long exposure to industrial dust. Carbonic anhydrase is the enzyme in RBCs that forms bicarbonate.
Answer: (A)
15. Quick Revision Summary
- Respiratory organs: body surface, cuticle, tracheae, gills, lungs (frogs also skin).
- Air path: nostrils → nasal chamber → pharynx → larynx → trachea → bronchi → bronchioles → alveoli; conducting vs exchange part.
- Inspiration: diaphragm and external intercostals contract; expiration normally passive.
- TV 500, IRV 2500–3000, ERV 1000–1100, RV 1100–1200 mL; VC = ERV + TV + IRV; TLC = VC + RV.
- pO₂ 104 (alveoli) → 40 (tissues); pCO₂ 40 → 45; CO₂ 20–25× more soluble.
- O₂: 97% as oxyhaemoglobin; sigmoid curve; Bohr effect. CO₂: ~70% bicarbonate (carbonic anhydrase), 20–25% carbamino-Hb, 7% dissolved.
- Control: medulla (rhythm), pons (pneumotaxic), chemosensitive area (CO₂, H⁺). Disorders: asthma, emphysema, occupational fibrosis.